Endo Belly: Causes, Symptoms, and What Helps


What is endo belly?
Endo belly is severe, visible abdominal distension that people with endometriosis develop, often within hours. The abdomen can swell to the point where it looks like a second-trimester pregnancy. It can stay that way for days, sometimes weeks, and then resolve as quickly as it came.
It is not gas or post-meal fullness. It is a clinical pattern tied to endometriosis-driven inflammation, hormonal cycling, and bowel involvement. Most people describe it as the most visible and most demoralizing symptom they live with.
Why it matters beyond the discomfort
People change their wardrobes around it. They cancel social plans. They get asked if they are pregnant by strangers and have to decide what to say. Treating endo belly as cosmetic bloating misses the point: it is a downstream sign that something inflammatory is happening in the pelvis, and that something often needs medical attention rather than a diet plan alone.
Why endometriosis causes severe bloating
The mechanisms are not fully mapped, but four factors are well-described in the literature.
Inflammation
Endometriosis is an inflammatory disease. Endometrial-like tissue outside the uterus bleeds on a hormonal cycle, irritates surrounding tissue, and triggers a chronic inflammatory response in the pelvis and abdomen. The result: fluid retention, swelling, and gas trapped in a digestive tract that is already slowed down by inflammatory mediators.
Hormonal fluctuations
Estrogen feeds endometrial tissue growth and ramps up inflammation. So endo belly tends to track the cycle. Many people see it worsen in the luteal phase and during menstruation, when hormonal swings are largest. Some see a second peak around ovulation.
Bowel involvement
Endometrial lesions can grow on the bowel surface or pull the bowel out of position through adhesions. Either way, normal motility breaks down. Constipation, diarrhea, urgency, and trapped gas all worsen distension. IBS frequently overlaps with endometriosis, which makes the picture even harder to untangle.
Fluid and cyst accumulation
Lesions can bleed cyclically into the pelvic cavity. That fluid adds to the distension. Endometriomas (cysts filled with old blood) on the ovaries can also contribute, especially when they grow large or rupture.
What to track
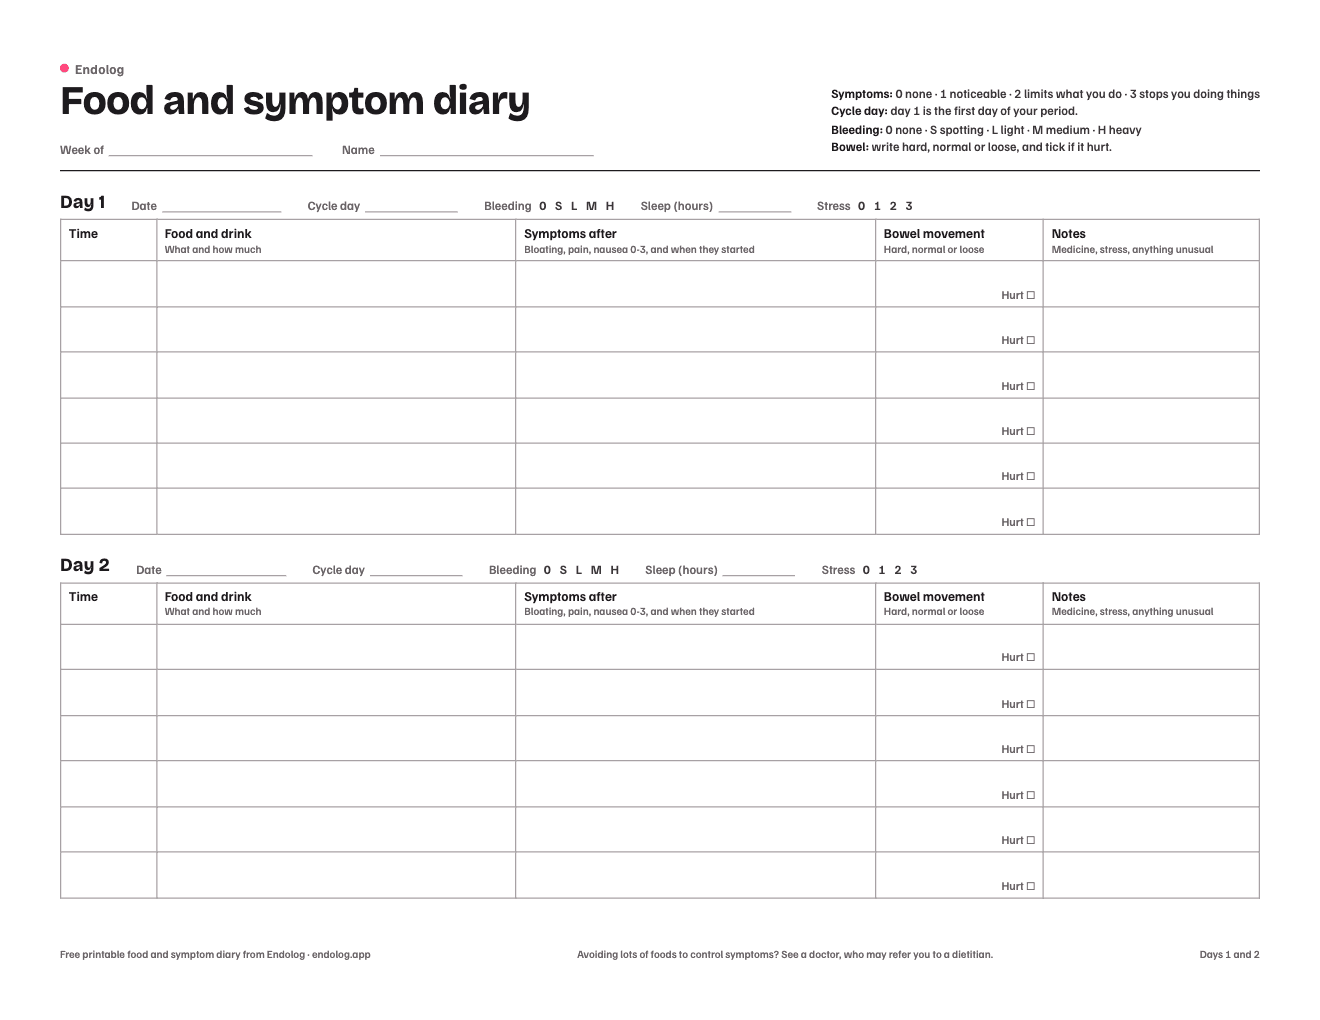
Tracking turns a vague "I bloat sometimes" into evidence a doctor can act on. The data points that matter:
Severity and duration
- Bloating intensity on a 1-10 scale, plus a visible-distension note (none, mild, "look pregnant").
- How long each episode lasts: hours, days, weeks.
- Whether it comes on suddenly or builds gradually across the day.
- Where in the cycle each episode falls.
Associated symptoms
Endo belly rarely arrives alone. Log:
- Pain: cramping, sharp, dull. Location and whether it radiates.
- Digestive: constipation, diarrhea, nausea, gas, changes in bowel habits.
- Fatigue: bloating days are often exhausting independent of pain.
- Mood: anxiety and low mood spike with severe distension for most people.
- Other endometriosis symptoms appearing on the same day. See the endometriosis symptoms guide.
Possible triggers
- Food: dairy, gluten, FODMAPs, carbonated drinks. A food diary alongside symptom logs is the only way to find your specific triggers.
- Stress: high-stress weeks often map to worse weeks.
- Activity: prolonged sitting often makes it worse; gentle movement often helps.
- Medications and supplements, especially new ones.
That data set is what makes pain diaries doctors will actually read different from a vague memory of "I felt awful last month." To log meals next to bloating and bowel symptoms, print the free food diary for bloating.
When to get evaluated
Endo belly itself is not an emergency. Specific combinations are.
Persistent or worsening pattern
If severity, frequency, or duration is climbing across cycles and what used to help no longer helps, that is a clinical signal worth bringing to a doctor. It may mean the disease is progressing, or that something new is going on.
Severe pain
New, sudden, or unrelieved abdominal pain alongside bloating can mean a ruptured cyst, bowel obstruction, or another acute problem. Do not wait that one out.
Bowel or bladder changes
Severe constipation, persistent diarrhea, blood in stool, difficulty urinating, or blood in urine alongside bloating all warrant investigation. Bowel and bladder endometriosis exist and need to be ruled in or out.
Unexplained weight change
Significant unintentional weight loss or gain with persistent severe bloating is a workup trigger regardless of endometriosis status.
Fever or signs of infection
Fever, chills, or vomiting with severe abdominal pain and bloating means same-day medical attention. Could be infection, could be torsion, could be something else acute.
What helps
There is no single fix. People settle on a combination of dietary, lifestyle, and medical strategies, and the right mix takes experimentation.
Dietary adjustments
- Anti-inflammatory eating: whole foods, vegetables, fish, olive oil, less ultra-processed food and added sugar. Helps a meaningful subset of patients in observational studies.
- Low-FODMAP elimination, ideally with a dietitian. Removes specific fermentable carbs for 2 to 6 weeks, then reintroduces them to find personal triggers. Not a long-term diet.
- Cutting individual triggers once identified. Dairy, gluten, and carbonated drinks are common offenders.
- Smaller, more frequent meals reduce the load on a slow digestive tract.
Lifestyle
- Stress management has a real effect on gut motility. Anything that lowers baseline stress helps.
- Walking and gentle movement help gas pass. Heavy abdominal work often does not.
- Heat on the abdomen helps pain and can reduce the muscular guarding that worsens distension.
- Adequate water intake. Dehydrated bowels are slow bowels.
Medical and complementary
- OTC anti-gas products, digestive enzymes, or IBS-targeted prescriptions for symptom relief.
- Hormonal therapy (combined pills, progestin-only methods, levonorgestrel IUD, GnRH agonists in selected cases) to suppress endometrial activity and lower inflammation.
- Pelvic floor physical therapy if pelvic floor dysfunction is contributing to bowel and pain symptoms.
- Probiotics: mixed evidence, but a low-risk experiment for many.
- Surgical excision of endometriosis lesions for severe or unresponsive disease, ideally with a surgeon who specializes in excision rather than ablation.
Bring this list to a doctor visit and ask which combination fits your specific case. The right answer changes depending on whether bowel involvement is suspected, whether you are trying to conceive, and what hormonal options you can tolerate.
Endo belly responds to systematic management more than to any single intervention. Tracking is what makes systematic management possible. Log endo belly episodes in Endolog and you will have months of data to bring to your next appointment.
Sources
- Low FODMAP diet, Cleveland Clinic
This article is general information, not medical advice. Read how we write and check our articles in our editorial policy.
Explore this topic
Related articles
October 8, 2026
Endo Belly Diet: What Helps and How to Find Your Triggers
No diet cures endo belly, but a short low-FODMAP diet with a dietitian can ease bloating. See what research shows and how a food diary finds your triggers.

October 30, 2026
Supplements for Endometriosis: What the Research Shows
Supplements for endometriosis: what trials found for vitamin D, vitamins C and E, melatonin, NAC and fish oil, the doses used, and who should be careful.

October 4, 2026
Cramps After Your Period: Causes and When to Worry
Cramps after period ends can be leftover womb cramps or ovulation, or a sign of endometriosis, a cyst or infection. Learn the causes and when to worry.
September 25, 2026
Cramps but No Period: Causes and When to See a Doctor
Cramps but no period? Take a pregnancy test if you could be pregnant. Learn the other causes, from ovulation to endometriosis, and when to see a doctor.
September 24, 2026
Where Are Period Cramps Felt? A Map of Period Pain
Period cramps are usually felt low in the belly and can spread to the back and thighs. See where period pain is located and which places need a doctor.

February 5, 2026
Ovulation Pain vs Endometriosis: How to Tell the Difference
Ovulation pain is a one-sided mid-cycle twinge that lasts up to 2 days. Learn how it differs from endometriosis pain and when to see a doctor about it.

Stop the medical gaslighting
Track pelvic pain, bleeding, digestive symptoms, fatigue, and flare patterns in one place. Endolog turns those daily logs into clean PDF reports you can bring to your next appointment.